Why so many women spend years without an answer
Lipedema is a chronic disorder of fat tissue that affects women almost exclusively. It typically appears as a symmetrical build-up of fat in the legs, hips and sometimes the arms, while the feet and hands stay comparatively slim. It is not caused by overeating, and it does not respond predictably to calorie restriction — which is precisely why it is so often mistaken for ordinary obesity or a lack of discipline.
The emotional cost is rarely part of the conversation. Women describe covering their legs in summer, avoiding photographs, skipping the beach, withdrawing from intimacy, crying in changing rooms. Many are weighed, lectured and sent home, visit after visit. Some are told the pain is anxiety. Being disbelieved about your own body is, for a lot of women, heavier than the swelling itself.
Signs women most often describe
No single sign confirms anything on its own, and several other conditions produce a similar picture. Still, these patterns come up repeatedly in patient reports and in the clinical literature:
- A clear disproportion between upper and lower body — a smaller waist with much fuller hips, thighs and calves.
- Legs that hurt, ache or feel bruised when touched, pressed or massaged.
- Bruises appearing with no memory of an injury.
- A “cuff” of tissue that stops abruptly at the ankle, leaving the foot unaffected.
- Heaviness and swelling that build through the day, in heat, or after long periods standing.
- Skin that feels nodular or grainy under the fingers, like small beads beneath the surface.
- Weight loss that visibly changes the face, chest and stomach but barely touches the legs.
- Other women in the family with the same shape and the same complaints.
What it is not
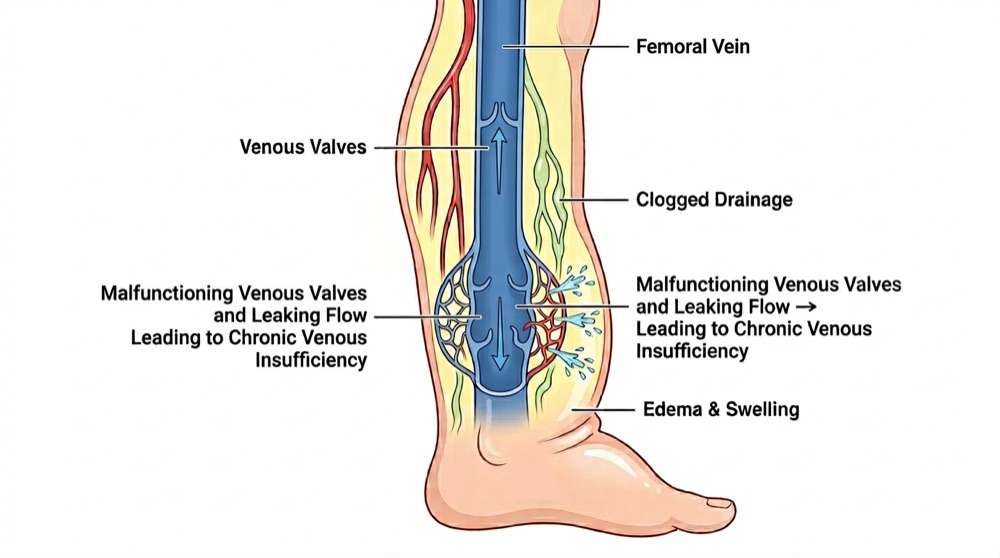
Lipedema is frequently confused with two different things. Lymphedema is a disorder of lymphatic drainage that usually involves the foot and is often one-sided or asymmetrical. Chronic venous insufficiency involves vein valves that no longer close properly, allowing blood and fluid to pool in the lower leg. All three can look similar from the outside, all three can coexist, and only a clinical examination can distinguish them.
What usually comes next
If the quiz reflects your experience, the constructive step is an evaluation with a professional who works with lymphatic and fat-tissue disorders — an angiologist, a vascular doctor, a certified lymphedema therapist, or a dermatologist experienced in this area. Written notes help: when the symptoms began, how they behave through the day, what changes with heat or standing, your family history, and what happened to your legs during past weight loss.
Care is generally conservative and long-term — movement, compression when indicated, manual lymphatic drainage, skin care, nutrition support, and attention to the emotional side of living with a chronic, visible condition. Approaches differ by country and by clinician, and every decision belongs with you and your doctor.
Common questions
Does this quiz diagnose lipedema?
No. It is an educational self-reflection tool. It cannot diagnose lipedema and it cannot rule it out. Its only purpose is to help you organise what you are experiencing before speaking with a professional.
Is lipedema the same as obesity or lymphedema?
No. They are distinct conditions that can resemble one another and can also occur together. Lymphedema typically involves the feet and is often asymmetrical; lipedema classically spares the feet and is symmetrical. Only a clinician can tell them apart.
Do you store or sell my answers?
No. The quiz runs entirely in your browser. Your selections are never transmitted to a server, never stored, and never linked to you. Closing the page erases them. See our Privacy Policy.
Can men have lipedema?
It is overwhelmingly reported in women, and hormonal life stages appear to play a role. Cases in men are described in the literature but are uncommon.
Can a supplement treat lipedema?
No. No dietary supplement treats, cures or reverses lipedema, lymphedema or venous disease. Some flavonoid-based supplements have been studied for general circulation and leg-comfort support, which is a different and much narrower claim. Any product discussed on this page is presented in that context only.
Reader question: what is Linfaflow?
Readers write in about products marketed for heavy, swollen legs, and one name comes up often enough that we looked at it: Linfaflow, a liquid herbal extract sold as “traditional lymphatic support”. This section is a paid placement and contains affiliate links. That does not change how we have written it: below is what the label states, what the published literature does and does not support for each ingredient, and what the advertiser claims that we could not verify.

- Category Dietary supplement — not a drug, not a medical device
- Format Liquid herbal extract, 2 fl oz / 60 ml dropper bottle
- Serving 1/4 teaspoon (1 ml); 59 servings per container
- Blend Proprietary blend, 300 mg per serving
- Extracts of Cleavers aerial parts (Galium aparine), Red clover flower (Trifolium pratense), Stillingia root (Stillingia sylvatica), Prickly ash bark (Zanthoxylum americanum)
- Other Vegetable glycerin, water
- Sold by The manufacturer, direct through its own website
Specification as published by the manufacturer at the time of writing. Daily Value (DV) is not established for this blend, and amounts of the individual extracts are not disclosed separately — a common practice with proprietary blends, and a real limitation when you try to compare a product against published research.
The four ingredients, and what the evidence actually shows
Cleavers (Galium aparine). A common hedgerow plant with a long history in Western herbalism as a “lymphatic tonic” and mild diuretic. That history is genuine and well-documented in traditional materia medica. The modern evidence is not: published work is largely phytochemical and laboratory-based, and we are not aware of controlled human trials measuring leg swelling, lymph flow or fluid retention with cleavers. Traditional use is a reason to study something; it is not evidence that it works.
Red clover (Trifolium pratense). The best-studied ingredient in the blend, though not for this purpose. Red clover isoflavones have been examined mainly in menopausal symptoms, where reviews report inconsistent and generally modest effects, and in lipid and bone endpoints. Evidence specific to oedema, lymphatic drainage or leg heaviness is thin. Red clover isoflavones are phytoestrogens, which matters for safety (see below) more than it does for swelling.
Stillingia root (Stillingia sylvatica). A plant used by 19th-century Eclectic physicians as an “alterative”, catalogued in sources such as King's American Dispensatory (1898). We could not identify modern controlled human trials of stillingia for any indication. Its presence here reflects a traditional formula, not a contemporary evidence base.
Prickly ash bark (Zanthoxylum americanum). Traditionally described as a circulatory stimulant. Published research on the Zanthoxylum genus is mostly preclinical — antimicrobial, anti-inflammatory and analgesic activity in laboratory models. Again, we found no human trials relevant to leg swelling.
About the “lymphatic drainage” framing
The lymphatic system returns fluid and proteins from tissue back to the bloodstream, and when it is impaired, fluid accumulates. That much is settled physiology. What does not follow is that drinking a herbal extract measurably improves lymph flow in a healthy or an impaired system. The lymphatic intervention with the strongest trial base is manual lymphatic drainage combined with compression, studied chiefly in lymphedema after breast cancer treatment — and even there, reviews describe benefits as moderate and dependent on the full decongestive programme, not on any single component.
What the manufacturer says — and what we could not verify
The advertiser's own website describes a 12-week observational study of 200 adults aged 35–68, and reports that a majority of everyday complaints such as leg swelling, puffiness and fatigue were linked to slowed lymphatic flow. We were unable to locate that study in any peer-reviewed journal or trial registry. Two things are worth holding on to: an observational study cannot establish that one thing causes another, and a study about a mechanism is not a study about a product. We report the claim because the advertiser makes it, not because we could confirm it.
The manufacturer also states that the product is sold directly through its own website, with a 30-day satisfaction guarantee. Pricing, shipping, guarantee terms and returns are set and administered by the manufacturer and shown on its site — not here.
Considerations before trying it
- Dietary supplements are not required to demonstrate efficacy before being sold, and they are not equivalent to prescription treatment.
- Red clover contains phytoestrogens. Anyone with a hormone-sensitive condition, or taking tamoxifen, hormone therapy or anticoagulants, should speak with a physician first.
- Cleavers is traditionally used as a diuretic. Combining it with prescription diuretics, or using it with kidney disease, warrants medical advice.
- Not for use in pregnancy or while nursing, or by anyone under 18.
- Persistent swelling, swelling in one leg only, or swelling with pain, redness or warmth needs medical evaluation — not a supplement.
- Nothing in this section is a treatment for lipedema, lymphedema or venous disease. No dietary supplement treats, cures or reverses any of them.
- Individual results vary, and some people notice nothing at all.
Reasonable to say
- Ingredients and serving size are disclosed openly on the label
- Simple traditional formula, one daily serving, liquid rather than capsules
- Sold direct, with published contact details and a stated guarantee period
- No stimulants, no alcohol; short ingredient list
Not reasonable to say
- That the blend has been tested in a published clinical trial — it has not
- That it treats or reverses any diagnosed condition
- That the cited 200-person study demonstrates the product works
- That individual ingredient amounts are known — they are not disclosed
Bottom line
Linfaflow is a traditional herbal formula sold into a category — heaviness, puffiness and evening swelling — where the demand is enormous and the good evidence is concentrated in other products entirely. If you want to try it, that is a legitimate personal choice; go in understanding that you are buying a traditional preparation with limited modern human data, not a tested treatment, and tell your doctor you are taking it. If your legs hurt when touched, bruise easily and resist weight loss, the priority is the evaluation described earlier on this page, not a bottle of anything.
References for this section
- Felter, H. W., & Lloyd, J. U. (1898). King's American Dispensatory — entries for Stillingia, Galium aparine and Xanthoxylum. (Historical source, documenting traditional use only.)
- Booth, N. L., et al. (2006). “Clinical studies of red clover (Trifolium pratense) dietary supplements in menopause: a literature review.” Menopause, 13(2), 251–264.
- Ghazanfarpour, M., et al. (2016). “Red clover for the treatment of hot flushes: a systematic review and meta-analysis.” Journal of Obstetrics and Gynaecology, 36(3), 301–311.
- Patiño, L. O. J., et al. (2012). “Zanthoxylum genus as potential source of bioactive compounds.” In Bioactive Compounds in Phytomedicine. InTech. (Preclinical review.)
- Ezzo, J., et al. (2015). “Manual lymphatic drainage for lymphedema following breast cancer treatment.” Cochrane Database of Systematic Reviews, (5), CD003475.
- Kakkos, S. K., & Nikolopoulos, G. K. (2018). “Efficacy of micronized purified flavonoid fraction in patients with chronic venous disease: a systematic review.” International Angiology, 37(2), 143–154.
- Pittler, M. H., & Ernst, E. (2012). “Horse chestnut seed extract for chronic venous insufficiency.” Cochrane Database of Systematic Reviews, (11), CD003230.
- Boyle, P., et al. (2003). “Meta-analysis of clinical trials of Cyclo 3 Fort (Ruscus) in chronic venous insufficiency.” Angiology, 54(Suppl 1), S1–S8.
These references describe the ingredient classes and comparator treatments discussed above. None of them studied this product, and citing them is not an endorsement of it by the authors or journals.
Preparing for the appointment
Women who are eventually evaluated properly tend to have one thing in common: they arrived with information already written down. Symptoms are hard to describe under pressure, and a ten-minute consultation rewards preparation. Before you go, put the following on a single page:
- When it started. Approximate age, and whether it coincided with puberty, a pregnancy, a change in contraception, or perimenopause.
- How it behaves through the day. Morning versus evening, heat versus cold, after long periods standing or sitting, after a flight.
- Pain. Whether the legs hurt spontaneously or only when touched, and how that affects sleep, work and walking.
- Weight history. What happened to your face, chest, waist and legs during any period of weight loss — this contrast is clinically informative.
- Family pattern. Which female relatives share the same body shape or the same complaints.
- What has been tried. Diets, exercise programmes, compression, drainage, medication — and what each one changed, if anything.
Questions worth asking
You are allowed to ask direct questions, and a good clinician will welcome them. Some that patients report finding useful:
- Based on the examination, does this look like lipedema, lymphedema, chronic venous insufficiency, or a combination?
- What in my examination points towards that conclusion, and what points against it?
- Do I need imaging or blood work to rule out other causes of swelling?
- Is compression appropriate in my case, and what type and class?
- Which specialist should manage this long-term, and can you refer me?
- What signs should make me come back sooner?
If you are told only to lose weight, without an examination of the tissue and without any of the above being addressed, asking for a second opinion is a reasonable step — not a difficult-patient move.
Where to find reliable information and support
Independent, non-commercial organisations publish patient guides, clinician directories and research updates. We have no affiliation with any of them and receive nothing from listing them:
- Lipedema Foundation — research funding and patient-facing explanations of the condition (US).
- Fat Disorders Resource Society — patient education and annual conferences on adipose tissue disorders (US).
- Lipoedema UK — charity providing information and support in the United Kingdom.
- Lymphatic Education & Research Network — resources on lymphatic disease, including lymphedema.
Peer support matters more than it sounds. Research on lipedema has documented significant appearance-related distress and higher rates of depressive symptoms among patients — not because of a personality trait, but as a predictable response to years of pain, visible change and being disbelieved. Addressing that side of it is part of proper care, not an optional extra.
Sources
- Kruppa, P., et al. (2020). “Lipedema — pathogenesis, diagnosis and treatment options.” Deutsches Ärzteblatt International, 117(22–23), 396–403.
- Buck, D. W., & Herbst, K. L. (2016). “Lipedema: a relatively common disease with extremely common misconceptions.” Plastic and Reconstructive Surgery – Global Open, 4(9), e1043.
- Herbst, K. L., et al. (2021). “Standard of care for lipedema in the United States.” Phlebology, 36(10), 779–796.
- Torre, Y. S., et al. (2018). “Lipedema: friend and foe.” Hormone Molecular Biology and Clinical Investigation, 33(1).
- Bertsch, T., & Erbacher, G. (2018). “Lipoedema — myths and facts, Part 1.” Phlebologie, 47, 84–92.
- Dudek, J. E., et al. (2018). “Depression and appearance-related distress in functioning with lipedema.” Psychology, Health & Medicine, 23(7), 846–853.
Sources are listed to show where the general statements on this page come from. They describe the condition in the medical literature; they do not evaluate any commercial product, and nothing here should be read as an endorsement by the cited authors or journals.
Advertising disclosure. This page carries paid placement. The section labelled “Sponsored content” is an advertisement and contains affiliate links; if you click through and make a purchase, we may receive a commission at no additional cost to you. Compensation does not change the quiz, the educational article or the sources cited, and we do not accept payment to remove stated limitations or criticism from a product write-up.
Medical disclaimer. The content on this page is general information and education only. It is not medical advice, it does not create a doctor–patient relationship, and it is not a substitute for consultation with a qualified healthcare professional. The self-assessment on this page does not diagnose any condition. Always seek the advice of your physician or another qualified provider with any questions about a medical condition, and never disregard professional advice or delay seeking it because of something you read here.
Supplement disclaimer. These statements have not been evaluated by the Food and Drug Administration. Any product referenced is a dietary supplement and is not intended to diagnose, treat, cure or prevent any disease. Individual results vary and are not guaranteed. Do not use as a substitute for prescribed treatment.
Urgent symptoms. Sudden swelling, swelling in one leg only, redness, warmth, skin breakdown, chest pain or shortness of breath require prompt medical attention. Do not use this page to delay care.
Editorial note. No statistics on this page are presented as precise figures for any individual, and prevalence estimates vary between published sources. This page contains no patient testimonials and no before-and-after imagery. Product images are supplied by the advertiser.